|
Eeman Abakura, Public Health Intern, NaRCAD Tags: Detailing Visits, Evidence Based Medicine, Mental Health  When we think about trauma-informed care, our minds naturally drift to the patient exam room. We think about providers modifying their clinical approach to ensure a patient who has experienced trauma feels safe, heard, and respected. But what happens when we turn that same compassionate lens inward toward the clinical teams themselves? Nadejda Razi Robertson, PhD, LCSW, Founder of Synergy Health Consulting, recently spotlighted a powerful evolution in our field known as “trauma-informed detailing” in her presentation Following the “Yes!”: Trauma-Attuned Detailing for Thriving Clinical Teams. As healthcare environments face unprecedented burnout, staffing shortages, and systemic stress, academic detailers must evolve. Rather than viewing detailing as simply delivering evidence and changing prescribing behaviors, Razi Robertson challenges detailers to see themselves as facilitators of psychologically safe conversations. Trauma-informed detailing expands the role of the detailer from an educator to a trusted partner who recognizes the emotional and organizational realities clinicians face while supporting meaningful practice change.  To understand why trauma-informed messaging matters in detailing, we have to look at the baseline data. Between 1995 and 1997, Kaiser Permanente and the Centers for Disease Control and Prevention surveyed more than 17,000 adults about experiences of abuse, neglect, and household challenges during childhood and their current health and behaviors. The findings showed that adverse experiences were common: nearly two-thirds of participants reported at least one adverse childhood experience (ACE), while 12.5% reported four or more. The landmark Adverse Childhood Experiences study taught the medical community that early trauma heavily correlates with lifelong physical and psychological health risks. Trauma-informed messaging to patients shifts the fundamental medical question from "What is the medical challenge you’re facing?" to "What would you like me to know about your life experiences, and well-being?" Today, detailers need to apply that same shift to the clinicians they detail. While ACEs describe the lasting impact of childhood adversity, many healthcare professionals experience an institutional equivalent through repeated exposure to chronic workplace stress, moral distress, workplace violence, and emotionally demanding patient care. Over time, these cumulative experiences can shape how clinicians respond to new information, interact with colleagues, and engage with practice change, making it essential for detailers to recognize the broader context in which learning takes place.  Clinicians and public health teams are carrying their own versions of chronic stress and institutional trauma. Burnout has reached unprecedented levels across the healthcare workforce, with studies reporting that nearly half of U.S. physicians experience symptoms of burnout characterized by emotional exhaustion, depersonalization, and a reduced sense of personal accomplishment (Shanafelt et al., 2012). Beyond burnout, many clinicians also experience moral injury, the distress that occurs when systemic barriers prevent them from providing the care they know their patients need. These realities affect more than clinician well-being; they influence learning, openness to change, and the ability to engage with educational outreach. If an academic detailer walks into a clinic demanding a change in prescribing habits without acknowledging the heavy mental load the team is carrying, the message is far less likely to resonate. A trauma-informed approach recognizes that the clinician's environment dictates their capacity to absorb new data. This perspective naturally complements the principles of academic detailing, which has always been rooted in relationship-building, active listening, and two-way dialogue rather than one-sided education. Trauma-informed detailing does not replace these principles; it strengthens them by intentionally fostering psychological safety, curiosity, and trust before introducing evidence. By acknowledging the realities clinicians face, detailers create conditions where meaningful conversations and sustainable behavior change become more likely. When adapting trauma-informed care to an academic detailing outreach strategy, Nadejda Razi Robertson's presentation, “Following the "Yes!": Trauma-Attuned Detailing for Thriving Clinical Teams” offers a practical approach grounded in presence, trust, and agility. Razi Robertson offers the following advice to detailers who want to adopt this approach:
In practice, this completely changes what face-to-face outreach looks like. A traditional detailing approach might lean on a more rigid pitch like, ‘Data shows our community’s rates of overdose are high, so we recommend you implement this new screening tool to identify patients who may have an opioid use disorder.’ A trauma-informed detailing message shifts the tone completely to incorporate presence and trust: ‘I heard you say that your team is stretched thin right now. How can I help you make this screening tool fit into your current workflow? What barriers are you seeing?’ When handling pushback, instead of saying, ‘I understand you're busy, but this guideline is the standard’, the agile detailer can say, ‘It sounds like adding another step feels completely unsustainable right now. Let’s look at how other clinics facing staffing shortages managed to automate this step’. When detailers give clinicians and clinical teams the grace, psychological safety, and collaborative choices that define trauma-informed care, they stop being outsiders who critique them, and become allies. This reimagines the role of the academic detailer not simply as someone who delivers evidence, but as an empathetic partner who helps healthcare teams navigate complex clinical decisions within equally complex environments. While evidence remains at the center of every detailing visit, how that evidence is delivered becomes just as important as the evidence itself. By pairing scientific rigor with empathy, flexibility, and trust, trauma-informed detailing creates the conditions for lasting practice change that benefits both clinicians and the patients they serve. Biography Aisha "Eeman" Abakura is a Biology major with a concentration in Neuroscience at Williams College. Her interests include neuroscience, public health, health communication, and the implementation of evidence-based interventions to improve healthcare outcomes. Through research and her experiences in education and community engagement, she has developed a strong interest in translating research into accessible resources for healthcare professionals and communities. Originally from Nigeria, Eeman is passionate about advancing health equity and improving access to high quality care through research, communication, and public health initiatives.
0 Comments
Anna Morgan, MPH, RN, PMP, NaRCAD Program Manager Tags: Conference, COVID-19, Deprescribing, Diabetes, E-Detailing, Older Adult Care, Health Disparities, HIV/AIDS, International, Jerry Avorn, Mental Health 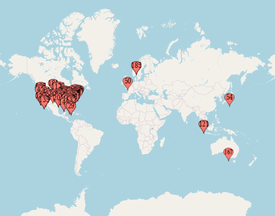 Map of where NaRCAD2020 attendees tuned in from Over 240 members of our worldwide community came together to be a part of something special--our 8th annual conference, and our first in a virtual setting. We were able to expand our reach and overcome barriers like travel time and financial constraints that have prevented our colleagues from attending previous conferences. There was a palpable sense of positivity, enthusiasm, and resilience, especially in a virtual space. We’re so proud of evaluations that cited a renewed sense of passion and commitment to AD based on the new lenses we applied to our programming, including comments about feeling “empowered” to continue this work in the year ahead (even amidst inevitable Zoom fatigue.)  Check out our highlights and access all event resources below and on the Conference Hub.
 With so many of you expressing a continued need around more of our peer working sessions, we’ll be focusing largely on that in 2021—we can’t wait to support your work this year. In the meantime, tell us what you need to make next year a success.
See you in 2021. The NaRCAD Team Have thoughts on our DETAILS Blog posts? You can head on over to our Discussion Forum to continue the conversation! A ROADMAP for Detailing Success: Improved Outcomes for the Medicaid Population in Oklahoma12/7/2018 Guest Blogger: Jacki Travers, PharmD Clinical Academic Detailing Pharmacist Pharmacy Management Consultants NaRCAD Training Alumnus Tags: Detailing Visits, Mental Health, Pediatrics In June of 2015, I had never even heard the term “academic detailing.” If you’d asked me to define it, I might have said it had something to do with the relationship between teachers and their cars. Little did I know that I was about to become an academic detailer, embarking on an exciting, rewarding, and sweaty-palmed journey to bring evidence-based materials to providers across the state of Oklahoma.
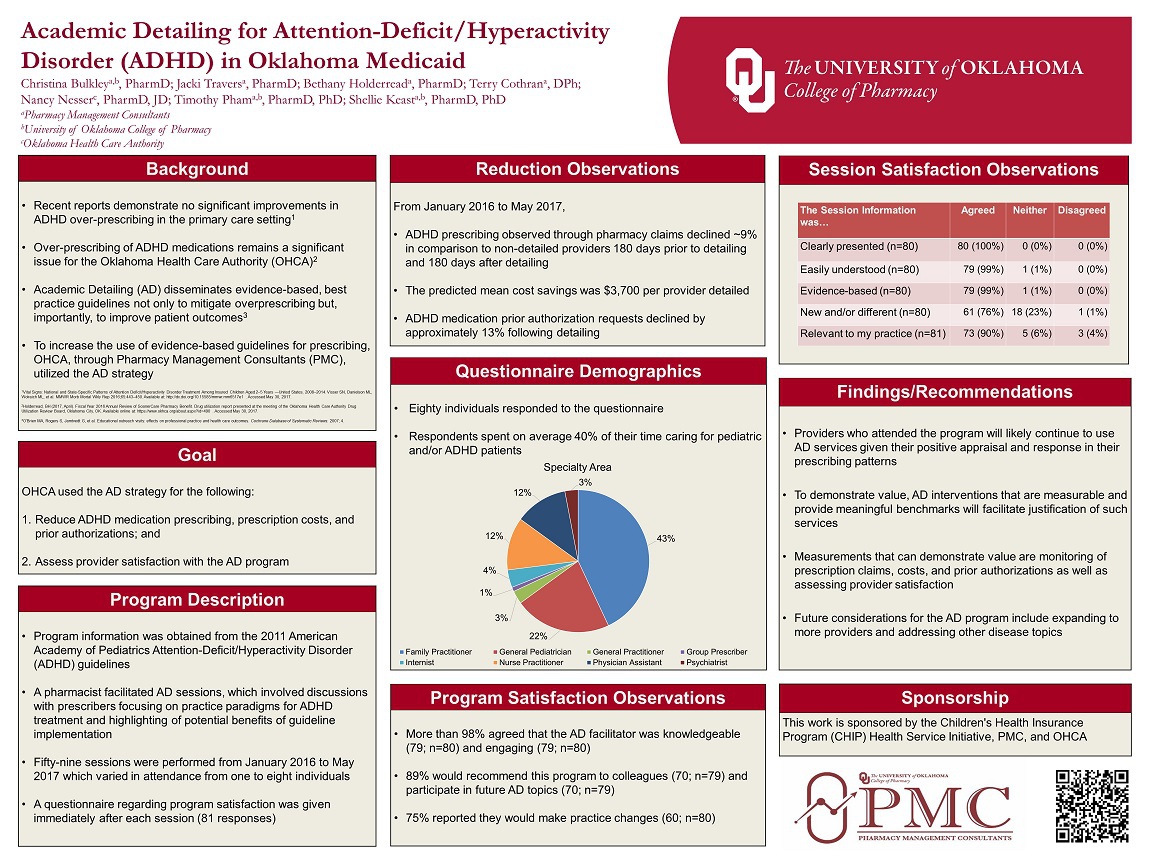
The Oklahoma Medicaid population is mostly under age 21. Detailing topics have included treatment of ADHD, use of atypical antipsychotic medications, and decreasing the use of antibiotics for treatment of upper respiratory infections. We are a small program by comparison, having one full-time detailer since 2015. We added one quarter-time detailer within the last year.  I will share some specific activities that worked for us, which creates a ROADMAP that has served us well and may help you as you begin or enhance your detailing efforts. R – Review When each set of materials neared completion, we asked the experienced NaRCAD staff to review our materials. Having an outside source helped clarify any confusion and identify ways to help the AD visit flow more naturally. O – Objectivity In identifying providers, we were making a bit of a judgement about their prescribing. As a detailer, I found it unhelpful to bring these judgements into the detailing visit. It is important for providers to see detailers as an ally for change rather than a source of punishment or criticism. A – Acceptance We surveyed providers’ acceptance of the program with each AD visit by asking them to evaluate the detailer and the materials. We also asked if they were willing to participate in future visits and recommend the program to colleagues. D – Define Defining the expected care gaps helped guide creation of our key messages. The treatment guidelines for ADHD are well established and remain unchanged since 2011. Comparing these guidelines to national and state patterns gave us a starting point for developing key messages. In addition to published guidelines, evaluation measures such as the Healthcare Data and Information Set (HEDIS) were very helpful. Doing this examination on the front end helped us begin with the end in mind and ensured we collected data we needed from the start. M – Motivational Interviewing Motivational interviewing (MI) is a communication style that is used to modify behavior. MI techniques helped us avoid some of the pitfalls that can accompany potentially confrontational conversations. A – Appealing Graphics We use Adobe Creative Cloud, which we find it to be very user-friendly. For someone with no graphic design experience, YouTube training videos were very helpful. We also use Pixabay as a source for ready-made graphics. All materials are open source and royalty free. We looked at the graphics used by other programs and even materials distributed by pharmaceutical representatives. Having appealing graphics is necessary for any AD program. P – People Having professional mentoring has helped move our program to the next level. Specifically, our detailers received invaluable preparation from the excellent NaRCAD Training Series. Moreover, I never miss the chance to learn from all the presenters and breakout participants at the International Conference each year. We are encouraged by the outcomes we have seen to date. The ADHD campaign produced a 58.33% reduction in medication claims for the very young (age 0-4) and cost savings of more than $226,000 across all ages. The antipsychotic campaign produced a 19.51% reduction in medication claims across all ages with associated savings of more than $365,000. I hope this snapshot of our program demonstrates that even small AD programs can show sizeable improvements in health outcomes and improve utilization of healthcare resources. Now, more than three years later, my understanding of academic detailing is much deeper and continues to grow with each new challenge. I was not completely wrong in my definition though: I absolutely see myself as a teacher and I certainly spend a lot of time in the car!
An Interview with Mass Mental Health CenterFeaturing Mark Viron, MD, adult psychiatrist & Director of Health Home Services at the Department of Mental Health’s Massachusetts Mental Health Center (MMHC) in Boston; Assistant Professor at Harvard Medical School. Tags: Materials Development, Mental Health, Smoking Cessation, Training NaRCAD: We’re excited to talk about your program because it focuses on such an important population, and such a specific topic that’s been a focus of public health initiatives across the nation. Tell us about Massachusetts Mental Health Center (MMHC).  Mark Viron: MMHC is a Department of Mental Health (DMH) community mental health center in Boston that has provided mental health services for over 100 years to people with chronic and persistent mental illness. Its ultimate goal is to help people maintain meaningful and productive lives in their community. In 2013, to better address the significant unmet primary care needs of our patients, we launched the Wellness and Recovery Medicine (WaRM) Center. The WaRM Center offers co-located and integrated wellness and primary care services for all MMHC patients.
NaRCAD: Why, historically, have rates of tobacco use been higher in folks with serious mental illness (SMI)? Why has there been resistance for clinicians to promote tobacco cessation for this group? Mark: It’s a complicated issue. There are risk factors that increase the rate of smoking in this group and these are coupled with obstacles to getting appropriate treatment. People with SMI are overrepresented among populations that face social and environmental conditions that are typically associated with an increased prevalence of smoking – poverty, unemployment, limited education, etc. Obstacles to quitting include limited availability of resources, lack of clinician involvement, and poor social/peer support.
 The strategy of AD: 1:1 clinician-facing outreach. NaRCAD: Agreed! What do these AD-focused, 1:1 visits between trained physician educators and psychiatric prescribers entail? Mark: The visits are 20-30 minutes long and follow the typical detailing visit structure. Visits are conducted by me, a psychiatrist at MMHC, or Gail Levine, MD, an internist and the Medical Director of our primary care clinic. We meet with the prescribers in their offices, and begin by asking open-ended questions to assess their needs and learn about their successes (and challenges) in addressing tobacco use with their patients. We celebrate successes and validate challenges, and then pivot to sharing evidence-based information and key messages that may help them address these issues with greater success. We conclude the visit by reviewing steps the prescriber can take to increase successful tobacco treatment, and provide a copy of our detail aid, along with a few high-yield references.  Click to see complete detail aid. A key ingredient to our success has been our detail aid. A great psychiatry resident (now attending), Kathryn Zioto, worked with Gail and me and the NaRCAD team to develop a detail aid about tobacco treatment in people with serious mental illness. The detail aid contains cutting-edge, evidence-based information in clear language with colorful graphics. It includes information about the MMHC’S Smoke Free Team, and highlights our three “asks”, which helps clinicians frame their conversations with patients:
NaRCAD: We enjoyed working on this important project with you, and we know how important great materials are in engaging clinicians to consider behavior change. That said, how have psychiatric prescribers been responding? Mark: The response has been quite favorable. It's been rewarding to sit down with colleagues and learn from their experience and expertise and to be able to offer some useful information about tobacco treatment and the Smoke Free Program. The one-on-one detailing encounters, even as brief as they are, give us quality time with our colleagues to focus on their individual concerns and questions. We probably get as much information as we give!
 NaRCAD AD Trainings: hands-on and interactive. NaRCAD: Two members of your team, yourself and Gail Levine, attended our AD Techniques Training in 2015 to prepare for this initiative. How has the training helped you provide this education to prescribers? Mark: Your training gave us an in-depth immersion into the world of academic detailing, helping us understand theories and evidence and think about implementation issues. Getting to practice detailing and getting feedback from experts in the field was invaluable, as was the ability to talk with people from around the country who are working on similar projects. NaRCAD's training is incredibly worthwhile – it was compact, comprehensive, and helped us acquire the needed skills to implement this project successfully.
 Provider education, engagement and activation are key, and AD provides a framework that has a proven track record in producing results in these areas. Plus, AD is efficient and easily implemented relative to other interventions--especially when you have assistance from NaRCAD! NaRCAD: Thanks for taking the time to connect with us. We’ve enjoyed helping to support this initiative with training and materials development! We look forward to continuing to learn about the impact you have on improving the health of people with serious mental illness, and sharing it with the community. We can't wait to hear more about this intervention at our conference this fall!  Biography. Mark Viron, MD is an adult psychiatrist and Director of Health Home Services at the Department of Mental Health’s Massachusetts Mental Health Center (MMHC) in Boston and an Assistant Professor at Harvard Medical School. He specializes in the treatment of psychotic disorders and the integration of primary and behavioral healthcare for people with serious mental illness.
He graduated from Tulane University School of Medicine and completed his psychiatry residency at the Massachusetts General Hospital/McLean Residency Program. He serves as an attending at MMHC’s partial hospital program, where he teaches and trains residents and medical students. He is also the project director for two grant-funded initiatives that aim to enhance MMHC’s ability to provide integrated primary and behavioral healthcare. |